
What it means
The head sitting in front of the shoulder line, with neck and shoulder pain by the end of the day.
Where it comes from
Hours looking at a screen carrying the cervical spine forward, holding the neck extensors in constant contraction.
How it is measured
It is measured on the side view, in the sagittal plane. The defining measurement is Where the head sits over the shoulder (Craniovertebral angle), and it is reported as a finding from below 50°. The number is computed from landmarks on that photograph — not estimated by eye, and not compared against a stock example.
What the numbers mean
| Measurement | Grade |
|---|---|
| 50° and above | Within normal range |
| 45–50° | Mild forward head |
| 40–45° | Moderate forward head |
| 40° and below | Severe forward head |
Source of the bands: Yip CHT, Chiu TTW, Poon ATK, Man Ther 2008;13:148-54 (CVA < 50° marks forward head posture)
What is usually seen alongside it
- Rounded upper back (Thoracic kyphosis) — above 45°
- Shoulders rolled forward (Scapular protraction) — above 3°
None of these is a diagnosis on its own. Together they corroborate the finding; apart, they do not refute it — a measurement nobody took counts neither for nor against.
What confirms it
The craniocervical flexion test, for deep neck flexor weakness.
Forward head and neck pain — what the evidence says, and what it does not
"Forward head posture causes neck pain" is repeated everywhere. The evidence is more careful than that, and its caution is more useful to somebody making a decision than a confident sentence would be.
What the systematic review found — and did not
Mahmoud and colleagues [1] pooled fifteen cross-sectional studies. Their result has two halves and usually only the first is quoted:
- In adults, those with neck pain show more forward head posture, and it correlates significantly with neck pain measures.
- In adolescents, no such association was found — neither between groups nor across most pain measures.
The authors conclude that age is an important confounder in this relationship. An adolescent's number cannot be read the way an adult's is.
And one study that found the opposite
Grob and colleagues [2] radiographed the necks of 107 people over 45 and split them by whether they had neck pain. No significant difference was found in global cervical curvature, in the segmental angles, or in how often a straight or kyphotic cervical spine appeared. Within the painful group, curvature was unrelated to duration, frequency, intensity, disability or radiating pain.
Their own sentence is blunt: such structural findings in someone with neck pain must be considered coincidental — not necessarily the cause. ⚠️ That does not sit alongside a promise to fix the pain by fixing the curve.
So what is the number good for
Comparison with yourself. The craniovertebral angle can be measured from a photograph with acceptable repeatability — Cote and colleagues [3] tested exactly that for photometric CVA, including when the assessment is done remotely.
So if you have a number today, the same measurement can be repeated in eight to twelve weeks and compared. What the number is not is a diagnosis of what is causing pain.
If you have neck pain, the treatment decision comes from an examination, not from an angle. This page explains the number; it does not replace a clinician.
References
- Mahmoud NF, Hassan KA, Abdelmajeed SF, Moustafa IM, Silva AG. The relationship between forward head posture and neck pain: a systematic review and meta-analysis. Curr Rev Musculoskelet Med. 2019;12(4):562–577. PMID 31773477 · DOI 10.1007/s12178-019-09594-y
- Grob D, Frauenfelder H, Mannion AF. The association between cervical spine curvature and neck pain. Eur Spine J. 2007;16(5):669–678. PMID 17115202 · DOI 10.1007/s00586-006-0254-1
- Cote R, Vietas C, Kolakowski M, Lombardo K, Prete J, Dashottar A. Inter and intra-rater reliability of measuring photometric craniovertebral angle using a cloud-based video communication platform. Int J Telerehabil. 2021;13(1):e6346. PMID 34345337 · DOI 10.5195/ijt.2021.6346
The evidence on this
Study summaries that measured this finding — with their numbers and their limits.
- How accurate is measuring posture from a photograph — Systematic review and meta-analysis, 29 studies
- How well does exercise work for forward head — Systematic review and meta-analysis, 13 randomised controlled trials
- Does bad posture mean pain — Systematic scoping review, 12 databases
- How smartphone use and neck pain are related — Systematic review and meta-analysis, 7 retrospective studies
- How heavy can a school bag be — Systematic review, 12 papers
The exercise programme
With the head forward of the shoulder line the deep neck flexors switch off while upper trapezius and levator overwork. The programme reverses exactly that.
The stages advance on a standard, not on the calendar:
- Stage 1 — release and wake up — weeks 1–4: Upper trapezius release, Levator scapulae stretch, Upper trapezius stretch
Move on: When the movement is done without pain and without compensating, and the stretch is no longer what limits it. - Stage 2 — control — weeks 3–8: Levator scapulae stretch, Upper trapezius stretch, Chin tuck — deep neck flexors, Wall angel
Move on: When the target muscle is felt through the whole range and the last set looks like the first. - Stage 3 — load and integration — weeks 6–16: Chin tuck — deep neck flexors, Wall angel, Standing posture reset
Move on: When the corrected pattern holds in everyday movement and under fatigue.
Each session 15–25 minutes, 4–6 times a week, for at least 12 weeks. (the training phases' default, not a study's result)
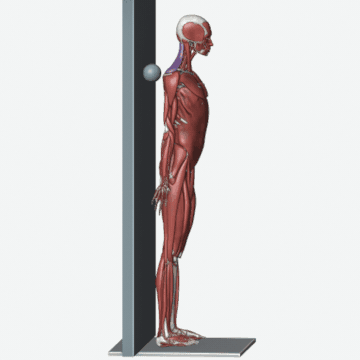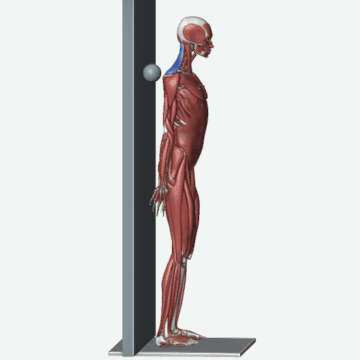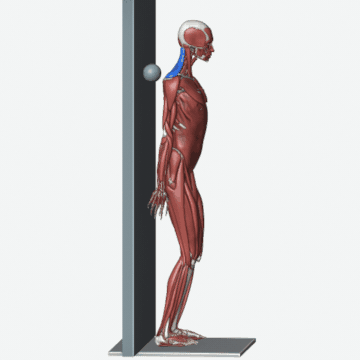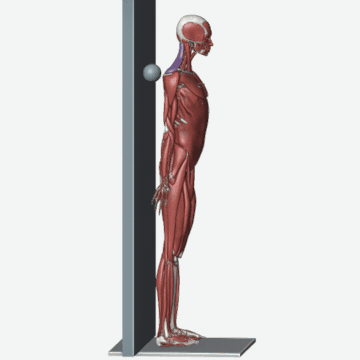
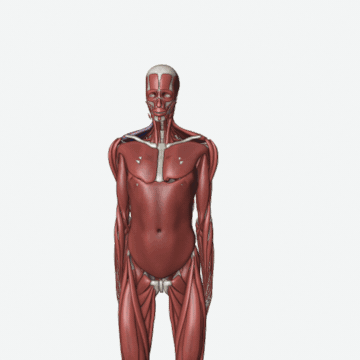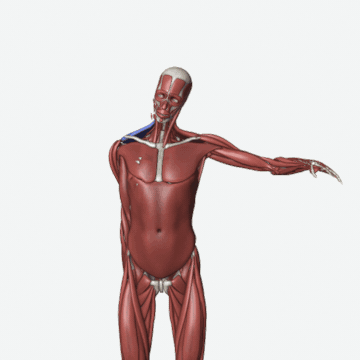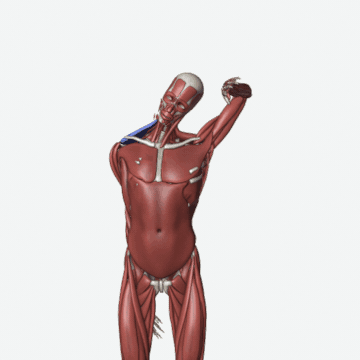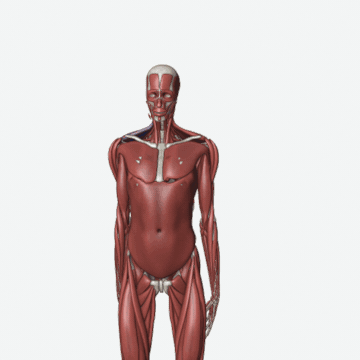
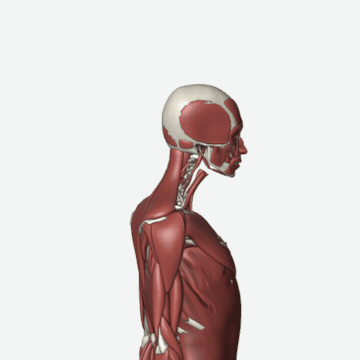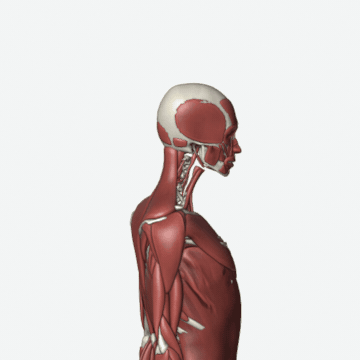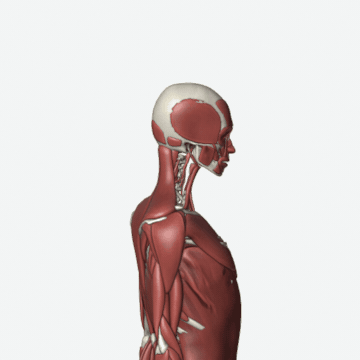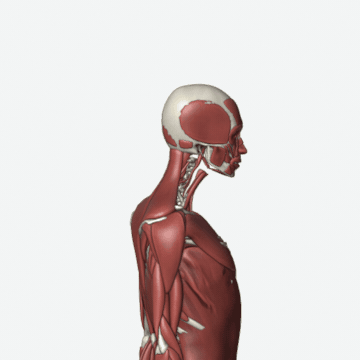
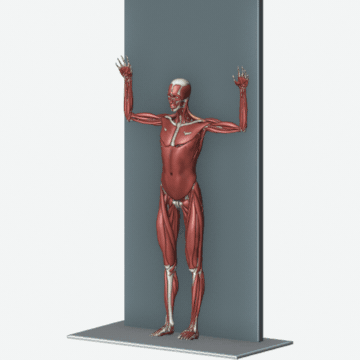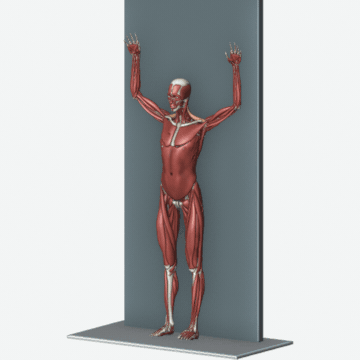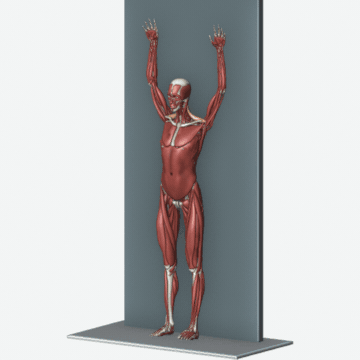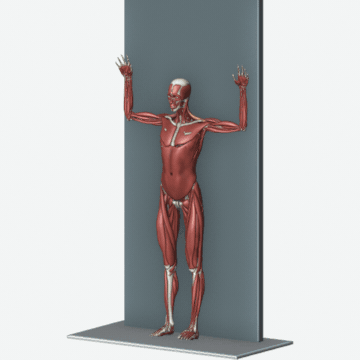
This example is for a moderate grade; each stage runs shorter or longer with the measured grade, and a person's own programme is written after assessment, around their other conditions and limits. If a movement causes pain, stop it and contact the clinic. Muscle colours in the animations: orange working, blue stretching, amber holding still.
Every number on this page is measured on the skin surface in a photograph. That is not the same as a measurement taken on a radiograph: it correlates with one and does not replace it. Wherever the decision depends on imaging, this page and the report itself say so.
What happens at the clinic
The assessment starts with three standing photographs — front, side and back. Every angle is measured on those photographs, the report prints the number and the grade for each, and the exercise programme is built from those numbers rather than from a template. Posture analysis explains the whole path, and the online assessment can be started from your own photograph now.
Frequently asked questions
At what point is forward head posture reported?
When where the head sits over the shoulder (craniovertebral angle) is below 50°, it is reported as a finding. That is where the "Mild forward head" band begins. The bands come from: Yip CHT, Chiu TTW, Poon ATK, Man Ther 2008;13:148-54 (CVA < 50° marks forward head posture)
Can forward head posture be assessed from a photograph?
A photograph gives a number, which most assessments do not have. But it is a surface measurement and it does not replace imaging. The craniocervical flexion test, for deep neck flexor weakness.
What is the most severe grade?
The worst band in this table is "Severe forward head". The grade is printed beside the measurement itself in the report, so it is always clear which number produced the word.