
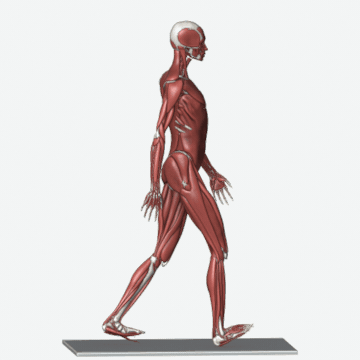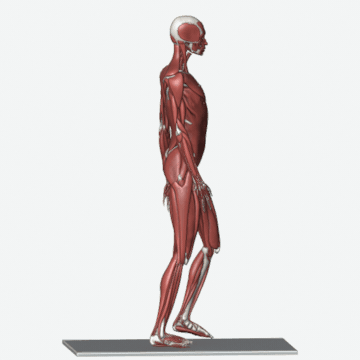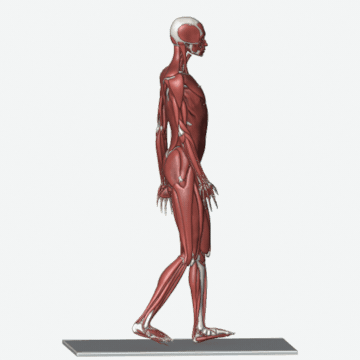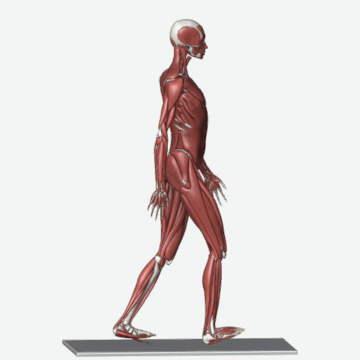
How to do it
Ten slow steps: heel contact, roll through the mid-foot, push off the big toe. Keep the pelvis level.
Default dose
10 · each side
This is the library's default dose. Each person's programme is set after assessment, around the grade of their finding and their own conditions and limits.
Where it sits in a programme: Integrate
The fourth phase is integration: using the new pattern in whole, everyday movements — standing, bending, squatting, walking — so the correction does not stay on the exercise mat.
Which postural findings it is prescribed for
It appears in the example programme on these pages:
Take care
- Multiple sclerosis — Only under supervision: Balance varies with fatigue and body temperature. The same movement is safe on a good day and not on a relapse day, so: beside something solid, and supervised.
- Parkinson's disease — Only under supervision: Postural instability and gait freezing make these the movements a fall happens in — and also the movements the training is for, so they stay, supervised.
- Stroke — Only under supervision: Asymmetric strength and proprioception mean the affected side will not hold the load the sound side does.
- Cerebral palsy — Only under supervision: Spasticity and limited joint range make correct performance different from person to person; that is an assessor's decision, not a list's.
- If the movement causes pain or makes pain worse, stop and contact the clinic or your doctor.
Source
Review article:
- Davis IS, Futrell E. Gait retraining: altering the fingerprint of gait. Phys Med Rehabil Clin N Am. 2016;27(1):339-55.
Review: retraining the gait pattern with external cues.