
What it means
A gap between the knees standing with the feet together, overloading the medial condyle.
Where it comes from
Lower limb axis misalignment driving the load line medial to the knee.
How it is measured
It is measured on the front view, in the coronal plane. The defining measurement is Knee alignment — bowed or knock-kneed (Hip-knee-ankle axis deviation), and it is reported as a finding from above 3°. The number is computed from landmarks on that photograph — not estimated by eye, and not compared against a stock example.
What the numbers mean
| Measurement | Grade |
|---|---|
| up to 3° | Within normal range |
| 3–6° | Mild bow leg |
| 6–10° | Moderate bow leg |
| 10° and above | Severe bow leg |
Source of the bands: Hip-knee-ankle deviation from straight; intercondylar distance beyond ~5 cm is the conventional tape threshold
What is usually seen alongside it
- Gap between the knees (Intercondylar distance) — above 5°
None of these is a diagnosis on its own. Together they corroborate the finding; apart, they do not refute it — a measurement nobody took counts neither for nor against.
What confirms it
Intercondylar distance with the feet together; a standing full-length radiograph for the true mechanical axis.
Bow legs — when it is normal and when it is not
Bow legs are usual in infants and children under one year. What matters is that the alignment resolves at the age it is expected to.
The normal timing
Yoo and colleagues [1], across 818 limbs, reported varus before one year, reaching neutral at around eighteen months, after which the knee moves towards valgus. Bow legs in a ten-month-old are expected; bow legs in a three-year-old are not.
⚠️ The same paper stresses that in its Korean sample the sequence ran later than earlier descriptions — so "late" should not be called abnormal in a hurry either.
The zero line is neutral. Below it is varus, above it is valgus, and the normal path starts below, crosses zero and rises. That is why the direction of travel matters as much as the number itself.
Why one universal table is not enough
Baruah and colleagues [2], across 1,020 children, write that the physiological range of the tibiofemoral angle is poorly defined and that this may lead to unnecessary therapeutic intervention, and that ethnic differences exist in the pattern. No published Iranian normative data is available.
What actually warrants a look
- Bow legs that have not resolved after two years, or that are worsening.
- Asymmetry: one knee clearly unlike the other.
- Pain, a limp, or stature disproportionately short for age.
These are not a list of diagnoses; they are a list of things worth looking at. The diagnosis comes from examination and, where needed, imaging.
References
- Yoo JH, Choi IH, Cho TJ, Chung CY, Yoo WJ. Development of tibiofemoral angle in Korean children. J Korean Med Sci. 2008;23(4):714–717. PMID 18756063 · DOI 10.3346/jkms.2008.23.4.714
- Baruah RK, Kumar S, Harikrishnan SV. Developmental pattern of tibiofemoral angle in healthy north-east Indian children. J Child Orthop. 2017;11(5):339–347. PMID 29081848 · DOI 10.1302/1863-2548.11.170047
The evidence on this
Study summaries that measured this finding — with their numbers and their limits.
- How accurate is motion capture from a phone camera — Systematic review and three-level meta-analysis, 12 studies
The exercise programme
The knee is pushed outward; the lateral chain is short while the peroneals and gluteus maximus are weak. The main work is the hip abductors and single-leg control rather than the knee itself — and the largest effect of all comes from changing the way the person walks.
The stages advance on a standard, not on the calendar:
- Stage 1 — release and wake up — weeks 1–4: TFL and lateral thigh release, Figure-4 buttock stretch, Calf and Achilles stretch, Soleus stretch (bent knee), Hamstring stretch
Move on: When the movement is done without pain and without compensating, and the stretch is no longer what limits it. - Stage 2 — control — weeks 3–8: Figure-4 buttock stretch, Calf and Achilles stretch, Soleus stretch (bent knee), Hamstring stretch, Glute bridge, Single-leg bridge, Side plank, Peroneal strengthening, Heel raise, Wall squat with knee control
Move on: When the target muscle is felt through the whole range and the last set looks like the first. - Stage 3 — load and integration — weeks 6–16: Glute bridge, Single-leg bridge, Hip hinge pattern, Single-leg deadlift, Side plank, Peroneal strengthening, Heel raise, Wall squat with knee control, Bodyweight squat, Controlled step-down, Split squat, Nordic hamstring exercise, Single-leg balance and squat, Gait pattern drill
Move on: When the corrected pattern holds in everyday movement and under fatigue.
Each session 20–30 minutes, 3–3 times a week, for at least 24 weeks. (from a study)
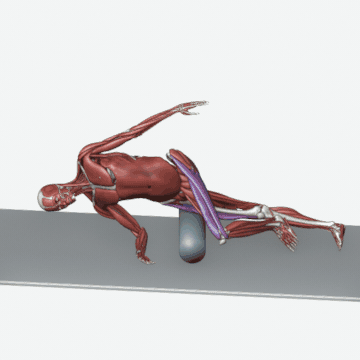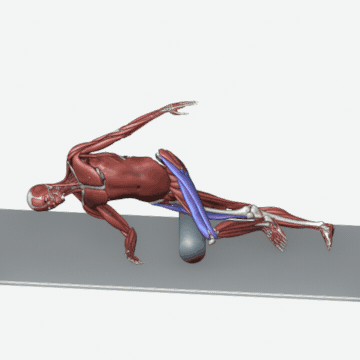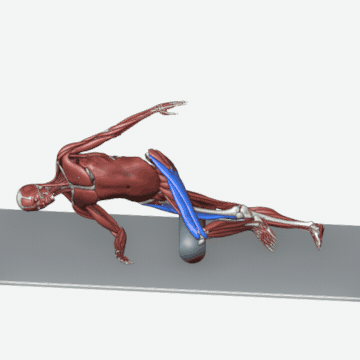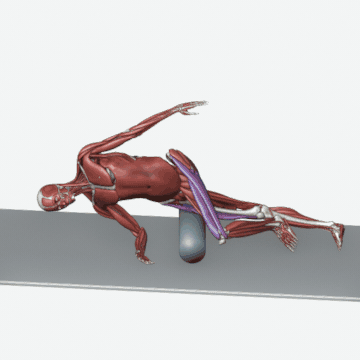
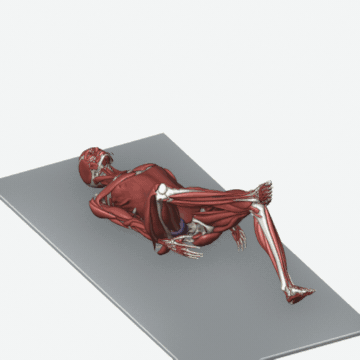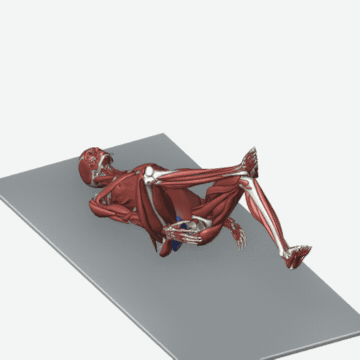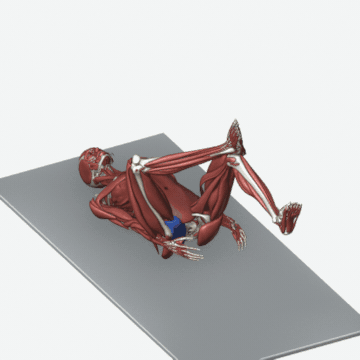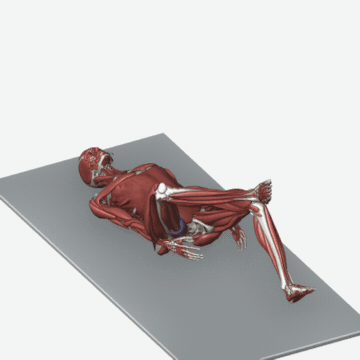
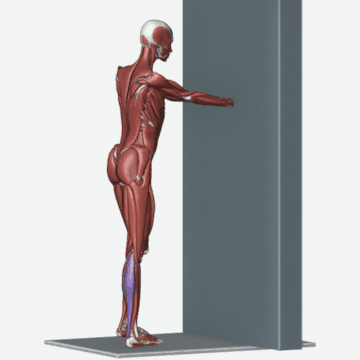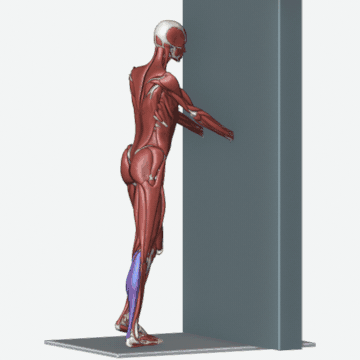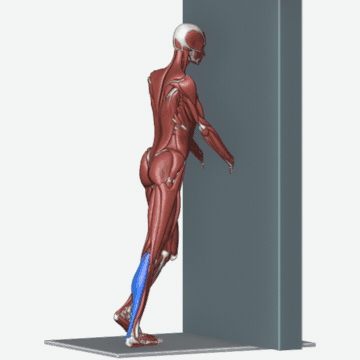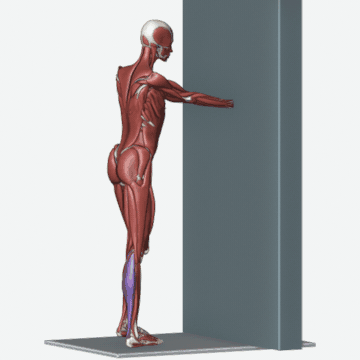
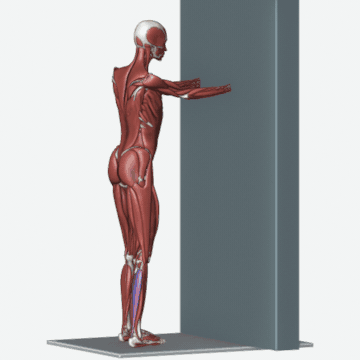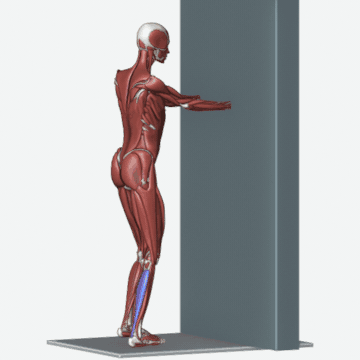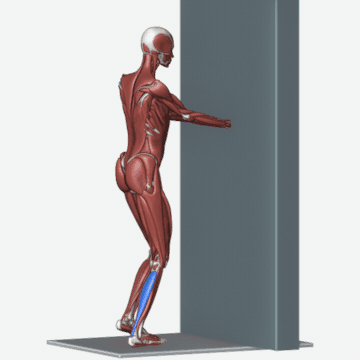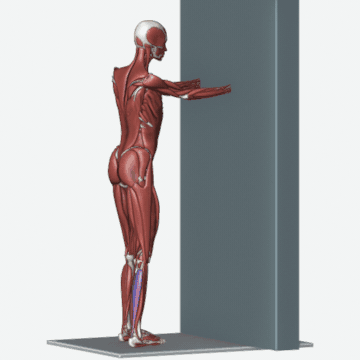
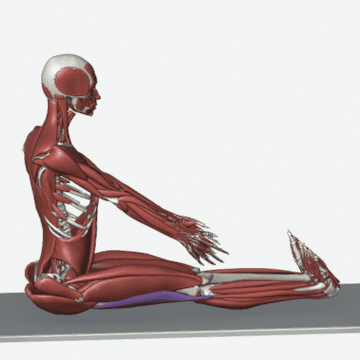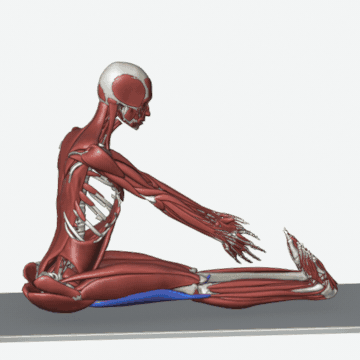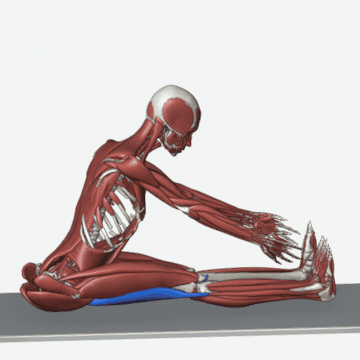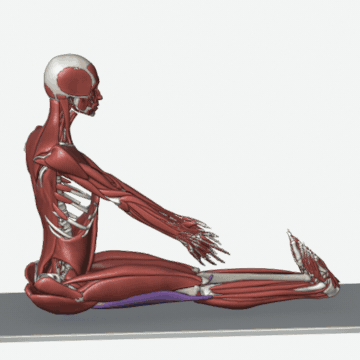

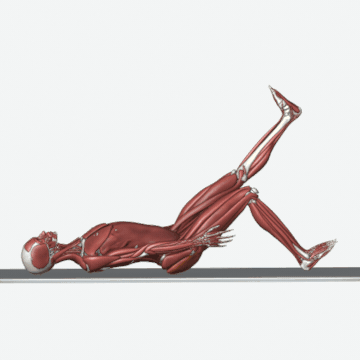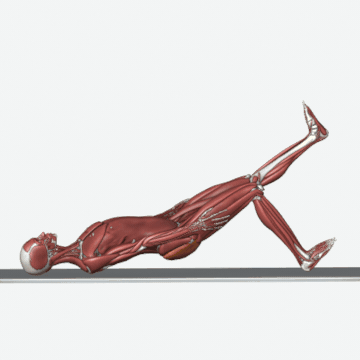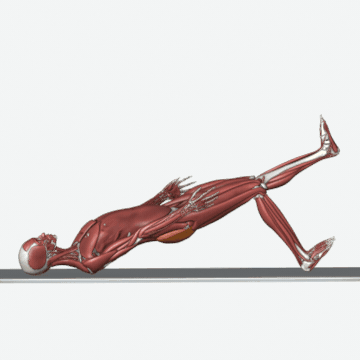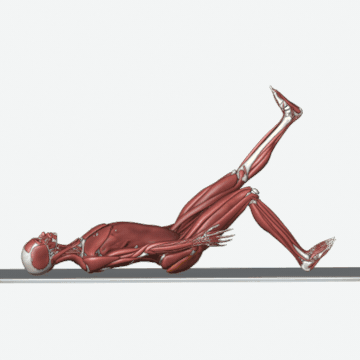

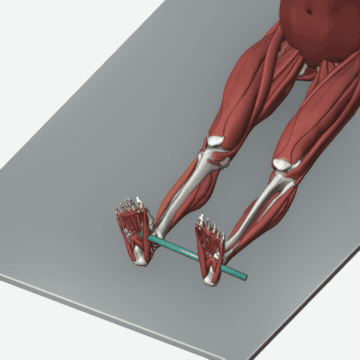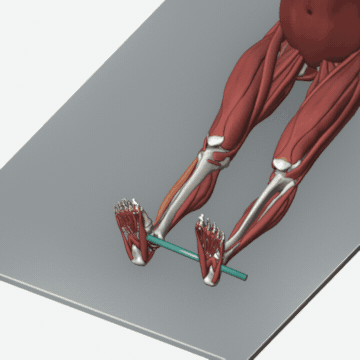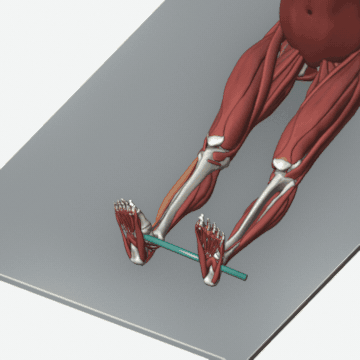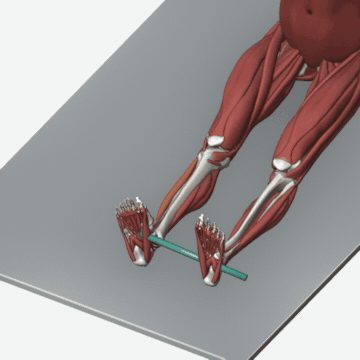
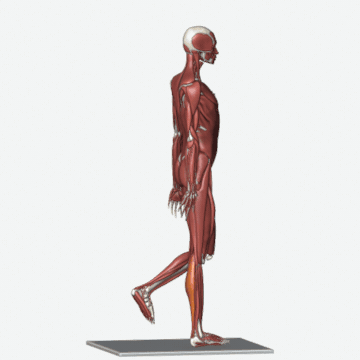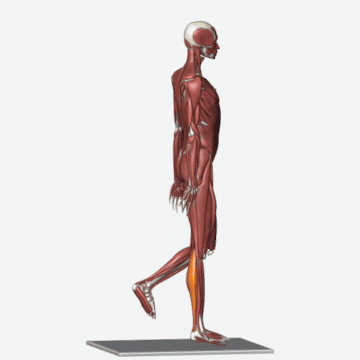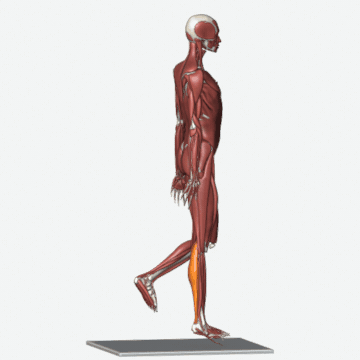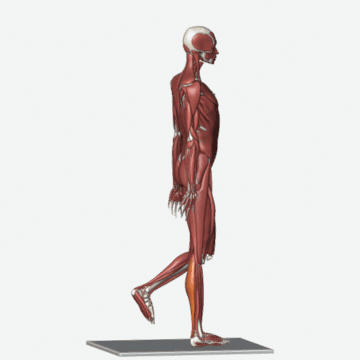
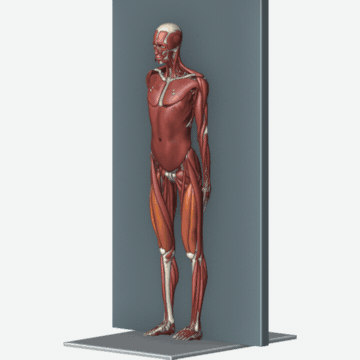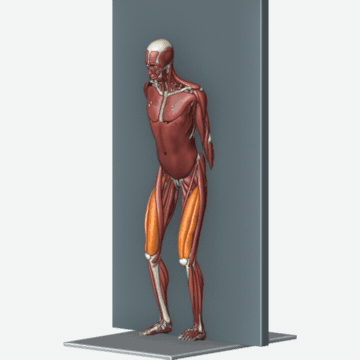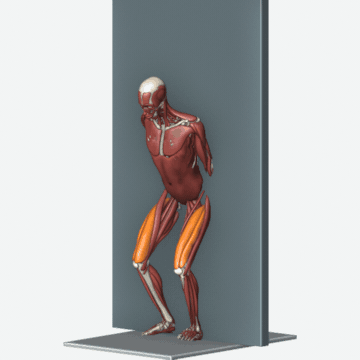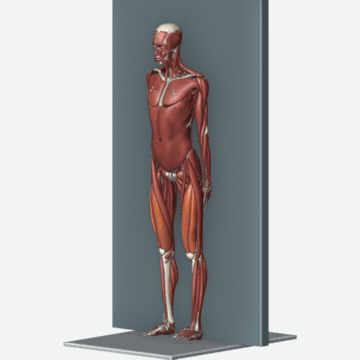
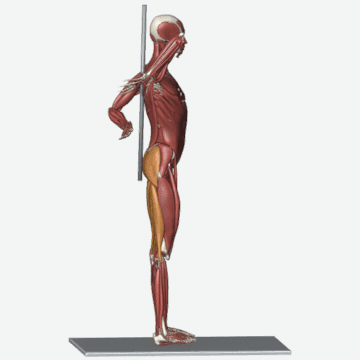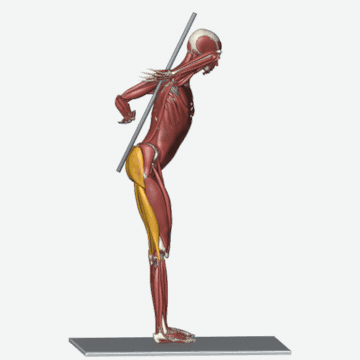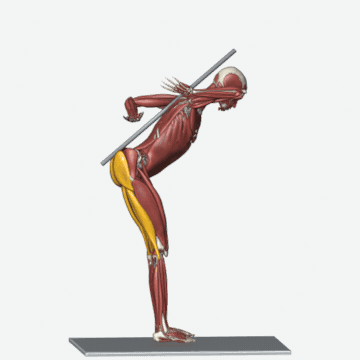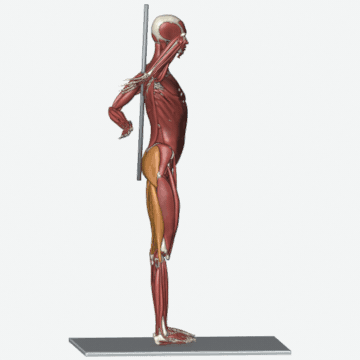
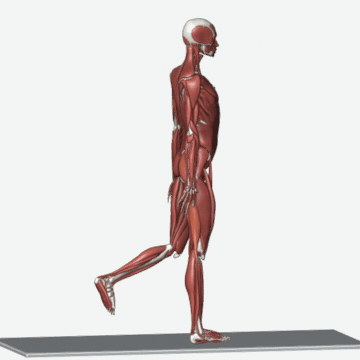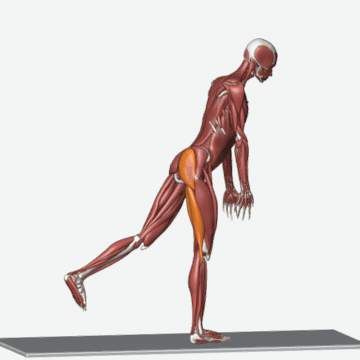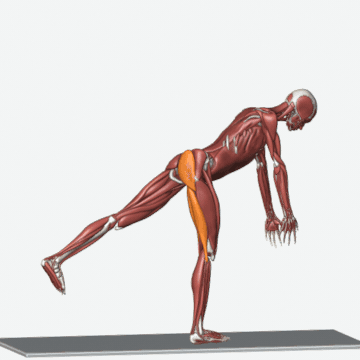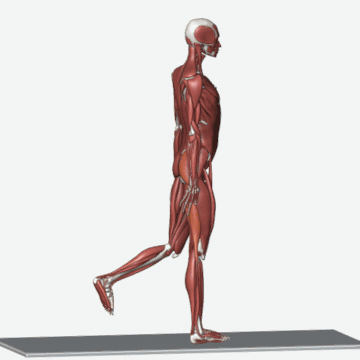
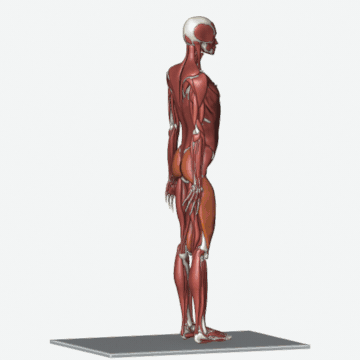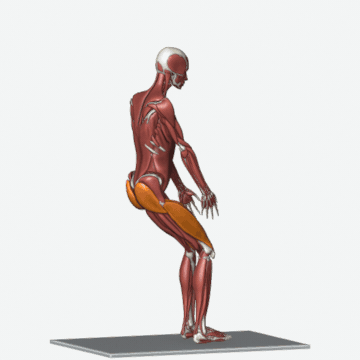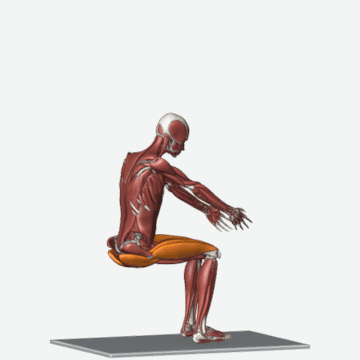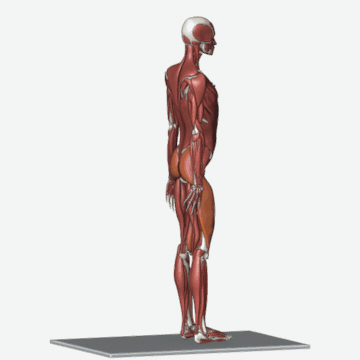
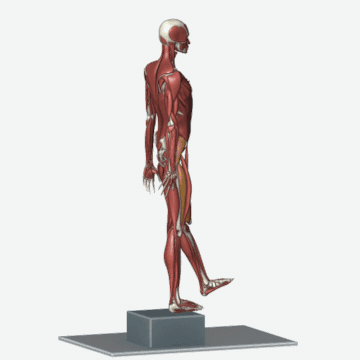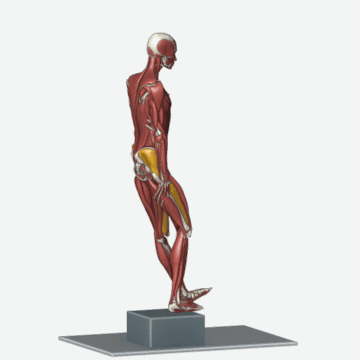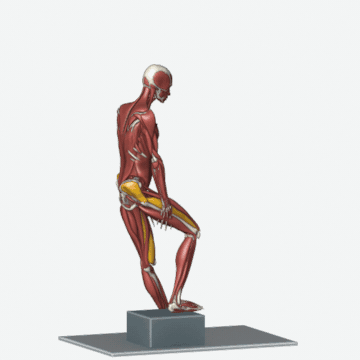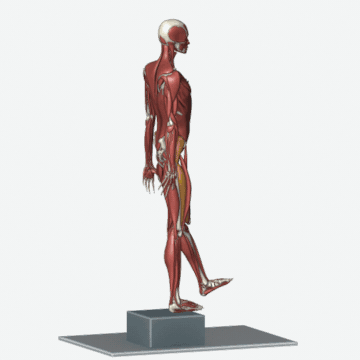
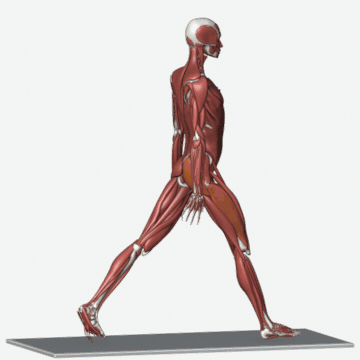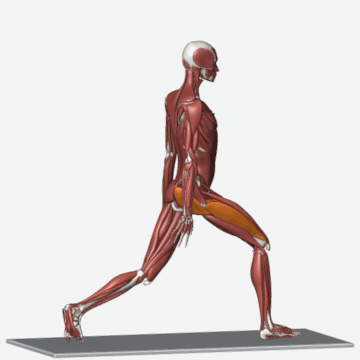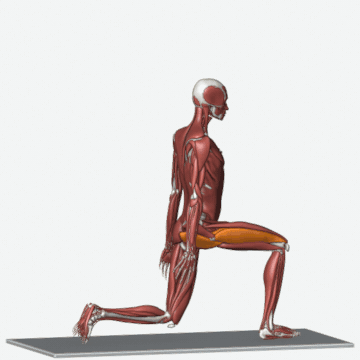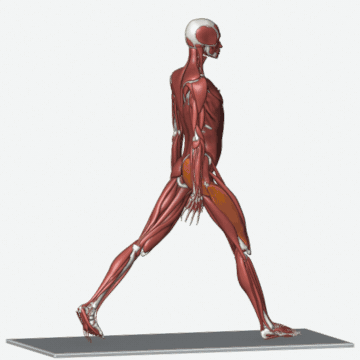
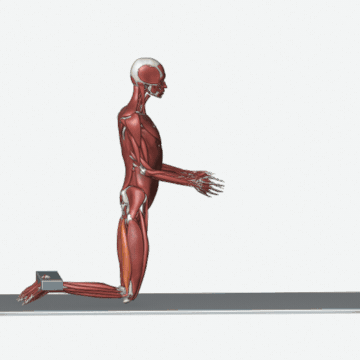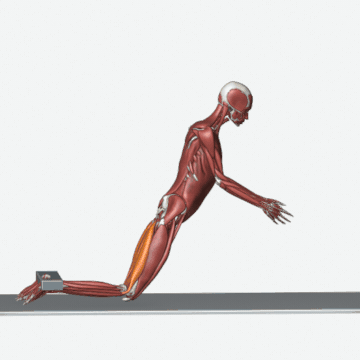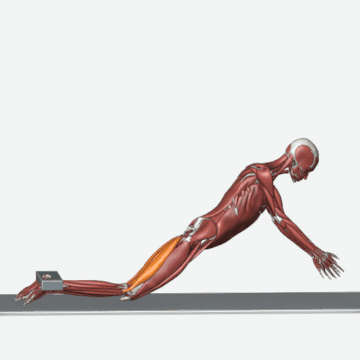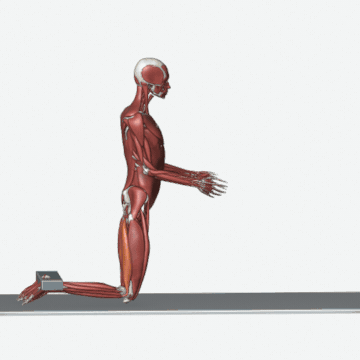
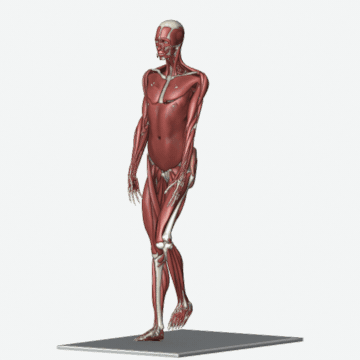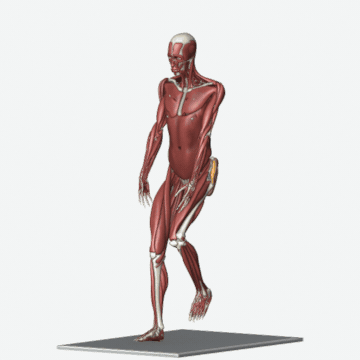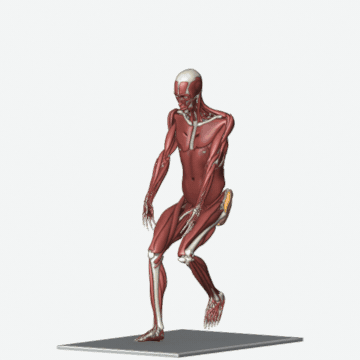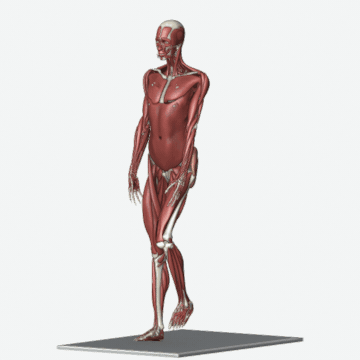
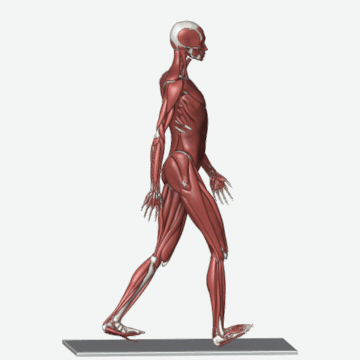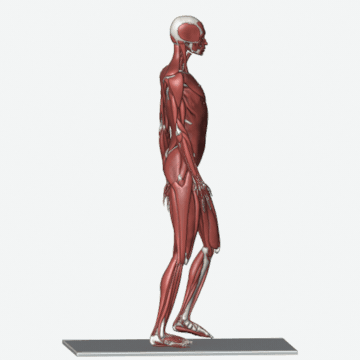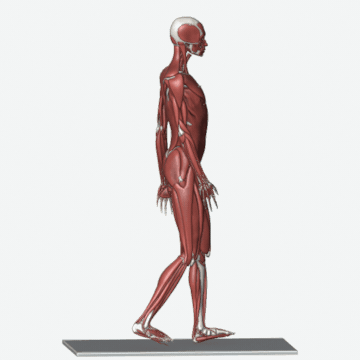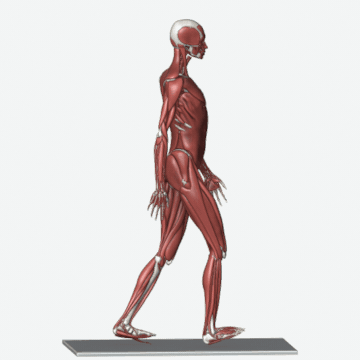
This example is for a moderate grade; each stage runs shorter or longer with the measured grade, and a person's own programme is written after assessment, around their other conditions and limits. If a movement causes pain, stop it and contact the clinic. Muscle colours in the animations: orange working, blue stretching, amber holding still.
Every number on this page is measured on the skin surface in a photograph. That is not the same as a measurement taken on a radiograph: it correlates with one and does not replace it. Wherever the decision depends on imaging, this page and the report itself say so.
What happens at the clinic
The assessment starts with three standing photographs — front, side and back. Every angle is measured on those photographs, the report prints the number and the grade for each, and the exercise programme is built from those numbers rather than from a template. Posture analysis explains the whole path, and the online assessment can be started from your own photograph now.
Frequently asked questions
At what point is genu varum reported?
When knee alignment — bowed or knock-kneed (hip-knee-ankle axis deviation) is above 3°, it is reported as a finding. That is where the "Mild bow leg" band begins. The bands come from: Hip-knee-ankle deviation from straight; intercondylar distance beyond ~5 cm is the conventional tape threshold
Can genu varum be assessed from a photograph?
A photograph gives a number, which most assessments do not have. But it is a surface measurement and it does not replace imaging. Intercondylar distance with the feet together; a standing full-length radiograph for the true mechanical axis.
What is the most severe grade?
The worst band in this table is "Severe bow leg". The grade is printed beside the measurement itself in the report, so it is always clear which number produced the word.